Benign skin lesion removal in Edinburgh
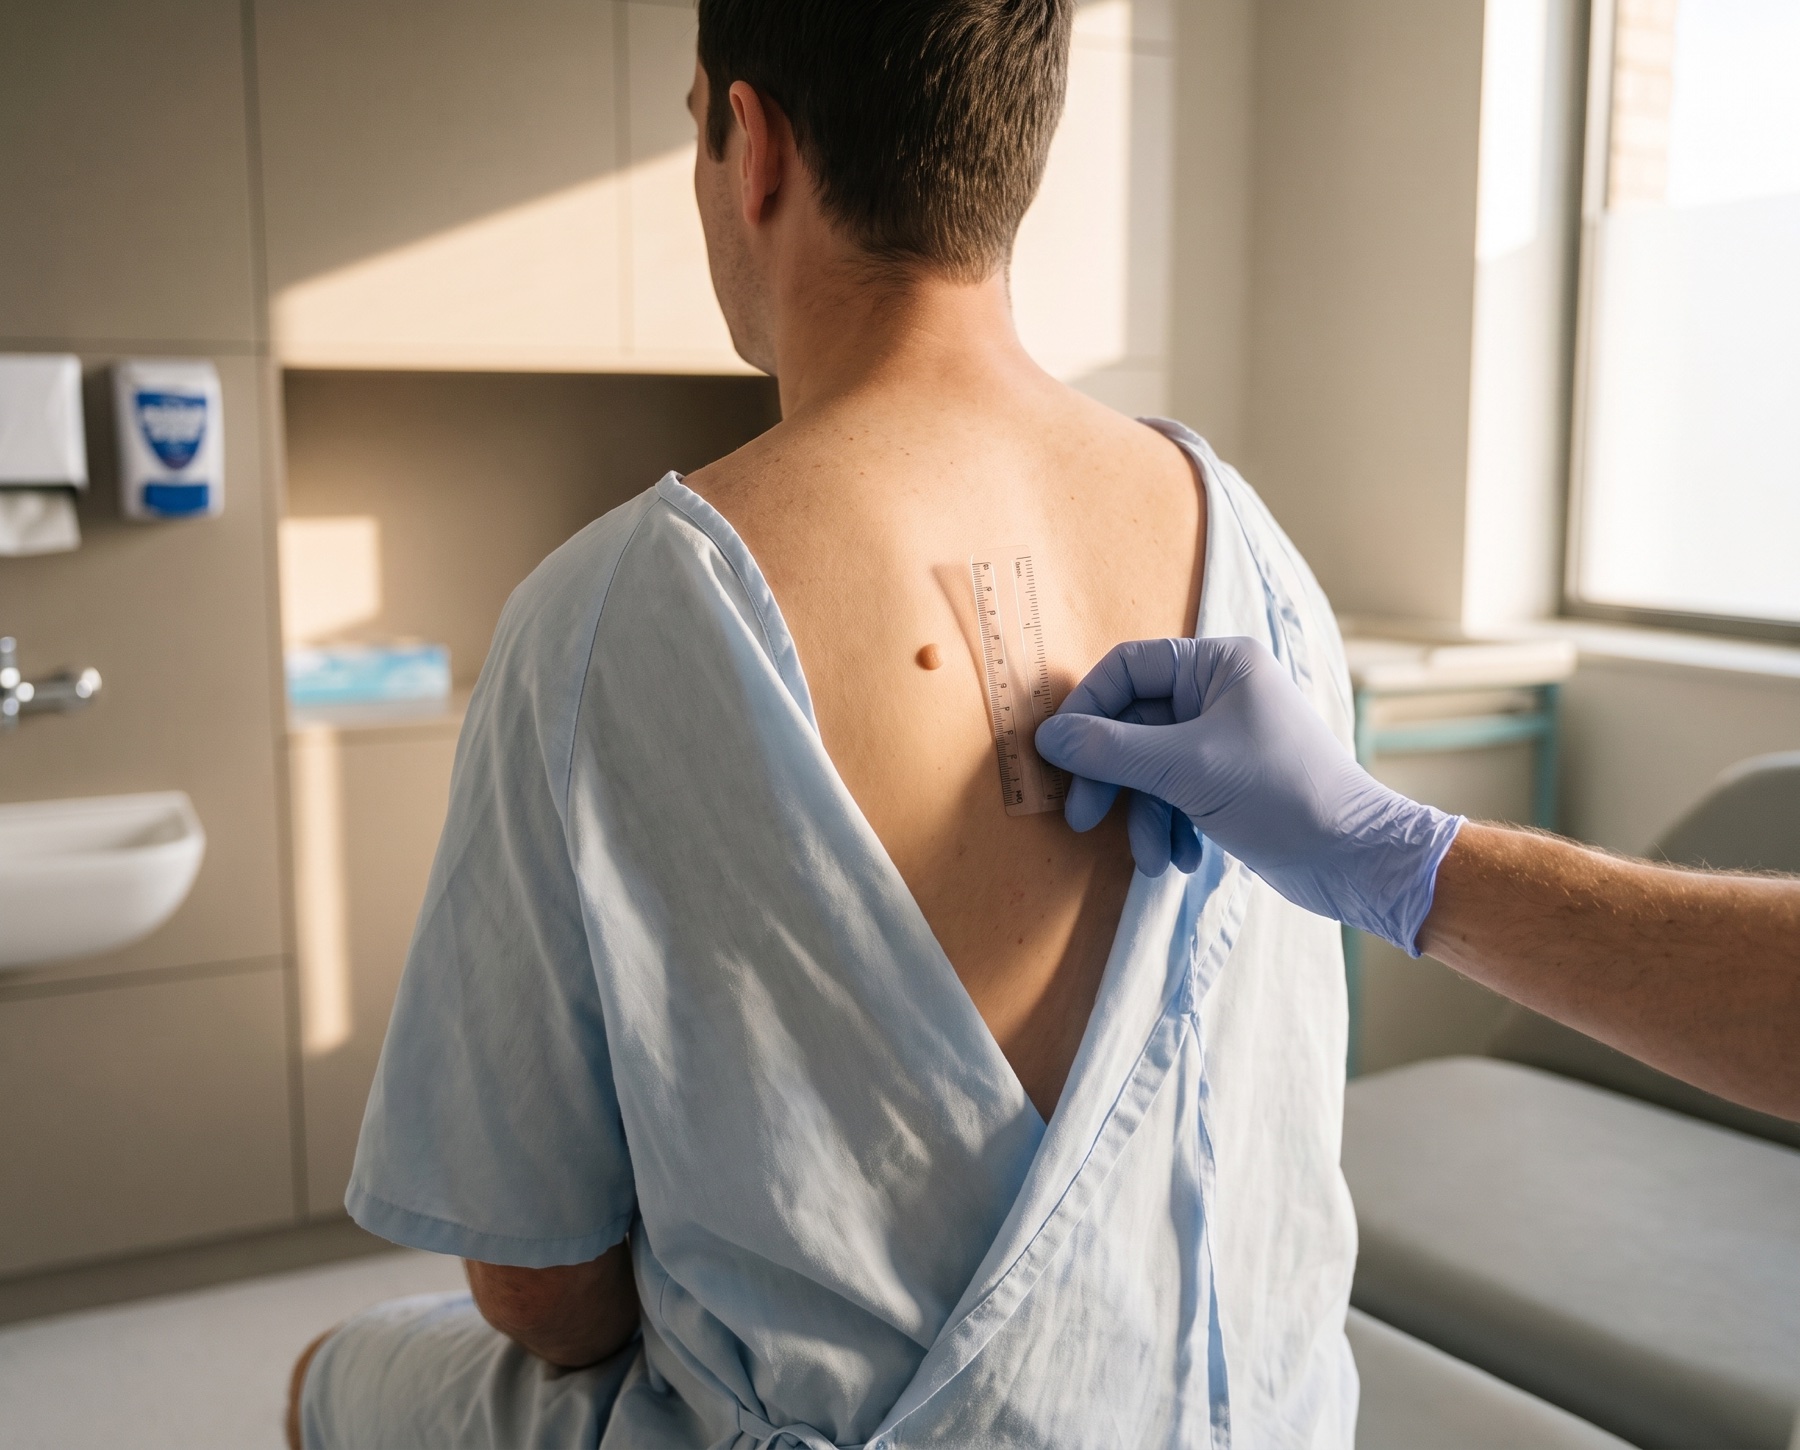
Moles, cysts, lipomas, skin tags and seborrheic keratoses are usually removed only when they catch, hurt or bother you. Every lesion is checked with dermoscopy first, and most are removed in one visit under local anaesthetic.
- Hospital stay
- Outpatient day case
- Recovery
- Typically 1 to 2 days, longer for larger lesions
- Histology
- Included on every excisional procedure
- Guide price
- From £395 (skin tag) to £2,500 (large cyst or lipoma). Full price list below
- First appointment
- Typically within 1 to 2 weeks
- GP referral
- Not required
- Your consultants


Contents
What benign skin lesions are
A benign skin lesion is any non-cancerous growth, mark, or lump in or on the skin. They are common, are not dangerous in themselves, and most are present for years before a patient decides to have one removed. People typically come in because a lesion has changed in appearance, has become uncomfortable, catches on clothing or jewellery, or simply because they no longer want it there.
The most common benign lesions removed at Waterfront are:
- Moles (naevi) — pigmented spots, flat or raised, present from childhood or developing in adulthood.
- Sebaceous cysts — firm, round lumps under the skin, often on the face, neck, scalp, or torso. Can become tender or infected.
- Lipomas — soft, fatty lumps under the skin, slow-growing, painless and mobile.
- Skin tags (acrochordons) — small soft growths, often in the neck, armpits, or groin.
- Seborrheic keratoses — raised, waxy or warty patches, common with age. See the dedicated page for detail.
- Dermatofibromas — firm, small, pigmented nodules, often on the legs.
Any pigmented or changing lesion is assessed with dermoscopy before removal, to confirm that the diagnosis is benign. Where dermoscopy or clinical appearance raises any concern about skin cancer, your consultant will recommend an excisional biopsy under the skin cancer pathway rather than a cosmetic removal. See the mole and skin cancer check page if your primary reason for booking is concern about a changing mole.
How removal is performed
The method is chosen at consultation, based on the type of lesion, its size, and its site.
Surgical excision — the lesion is removed in full with a small margin of surrounding tissue, and the wound closed with sutures. Used for moles, cysts, lipomas, and any lesion where histology is required. The excised material is sent for histology in every case.
Shave excision — a horizontal removal of a raised lesion at the level of the surrounding skin. Used for raised moles and similar lesions where a flush result is preferred and the lesion is clinically benign. Material is sent for histology.
Cryotherapy — freezing with liquid nitrogen, used for some skin tags, smaller seborrheic keratoses, and similar superficial benign lesions. Does not produce material for histology, so is only used where the clinical diagnosis is certain.
Curettage and cautery — scraping the lesion off and sealing the base with electrocautery. Used for some seborrheic keratoses and similar superficial lesions.
Most procedures are performed under local anaesthetic in a single outpatient visit. Larger lipomas, multiple lesions in one session, or removals in anatomically challenging sites may be planned under general anaesthesia. Reconstruction is occasionally needed where a lesion is large or in a cosmetically sensitive site; this is planned in the same procedure by the same consultant.
When to seek assessment
Patients commonly book a benign lesion removal when they have noticed:
- A lump or lesion that catches on clothing, hair, or jewellery
- A lesion that has become tender, painful, or has become infected
- A lesion that has grown larger over time
- A lesion that is cosmetically bothersome
- A skin growth they would prefer to have checked and removed in a single appointment
Any lesion that has changed in size, shape, colour, or behaviour, or that bleeds, itches, or crusts repeatedly, is assessed under the skin cancer pathway rather than as a cosmetic removal.
What benign lesion removal can and can’t do
Removing a benign lesion is a choice, not a need, and it swaps a lump or mark for a scar. We would rather you made that choice knowing what the scar will look like.
It can
- Check the lesion with dermoscopy first and confirm the diagnosis, with histology on everything we excise.
- Remove moles, cysts, lipomas, skin tags, seborrheic keratoses and dermatofibromas, most in one visit under local anaesthetic.
- Choose the method, excision, shave, curettage or freezing, that suits the lesion and the site.
- Place the scar along the natural skin lines wherever the site allows.
It can’t
- Be done without a scar. Excision leaves a line a little longer than the lesion; shave, curettage and freezing leave a flat patch that is lighter or darker than the skin around it.
- Promise it will not come back. Recurrence is uncommon after a complete excision, but more likely after shave, curettage or freezing, which leave the base behind.
- Stop new lesions. Cysts, lipomas, skin tags and keratoses go on forming in people prone to them.
- Guarantee how the scar will heal. Site, skin type and your own healing all matter, and some sites, such as the chest, shoulders and upper back, scar more thickly.
- Replace the skin cancer pathway. Anything that is changing, bleeding or uncertain is removed as an excisional biopsy with margins, not as a cosmetic removal.
Your consultant will tell you at your consultation which of these apply to you.
Risks, and how often they happen
Every procedure carries some risk. Here they are in three groups. Your consultant will go through them with you, and they are in your written consent.
Expected Almost everyone, and they settle
-
A scar, a little longer than the lesion after excision, or a flat patch after shave, curettage or freezing. It is red or pink at first and fades over 12 to 18 months.
-
A patch that heals lighter or darker than the surrounding skin, more noticeable in darker skin and on sun-exposed sites.
-
Swelling and bruising around the wound for the first one to two weeks.
-
Discomfort for a day or two, eased by simple painkillers.
-
Numbness or altered sensation around the scar, which usually settles over weeks to months and occasionally persists.
Uncommon Some patients, and some need further treatment
-
Wound infection that needs a course of antibiotics.
-
Bleeding after surgery that needs pressure, a dressing change or a return to have the wound checked.
-
The lesion coming back, after shave, curettage or freezing, or where part of a cyst sac was left. It can be treated again.
-
A raised, thickened scar (hypertrophic or keloid), more likely on the chest, shoulders, upper back and earlobes and in darker skin. It can be treated but not always fully flattened.
Rare but serious
-
An unexpected histology result, which your consultant discusses with you in person and, where needed, hands to the skin cancer pathway.
-
Injury to a nerve beneath the skin on the face, neck or wrist, which can cause lasting numbness or, rarely, weakness of a nearby muscle. Your consultant plans around the known danger zones.
-
A serious reaction to the local anaesthetic.
-
A serious reaction to a general anaesthetic, where one is used for a large lipoma or several lesions at once.
For the long term
-
Scars keep changing for a year or more. Protect a new scar from the sun for the first year, and tell us if it thickens.
-
New lesions can appear, and each is a separate decision. Any lesion that changes should be checked whether or not you have had one removed.
-
More on each lesion is on our mole removal, cyst removal, lipoma removal, skin tag removal and seborrheic keratoses pages.
-
Figures for each condition are on the pages for mole removal, cyst removal, lipoma removal, skin tag removal and seborrheic keratosis removal.
Where these figures come from
- Dixon et al., Dermatol Surg 2006;32:819-826 (5,091 lesions, no prophylactic antibiotics). For: Wound infection.
- Dixon et al., Br J Surg 2007;94:1356-1360 (5,950 skin cancer excisions). For: Bleeding after surgery.
- British Association of Dermatologists, Keloids patient leaflet (Apr 2021). For: Raised (hypertrophic or keloid) scars.
- NHS, Local anaesthetic (reviewed Dec 2025). For: Serious reaction to local anaesthetic.
- West Suffolk NHS Foundation Trust, Risks associated with your anaesthetic: anaphylaxis (source: Royal College of Anaesthetists). For: Anaphylaxis under general anaesthetic.
- Worcestershire Acute Hospitals NHS Trust patient leaflet. For: Death under anaesthetic.
- Bong and Perkins, Dermatol Surg 2003;29:227-229. For: Regrowth after shave of a mole.
- Mehrabi et al., Dermatol Surg 2002;28:673-677. For: Cyst recurrence.
- British Association of Dermatologists, Cryotherapy patient leaflet (Oct 2022). For: Pigment change after freezing or shave.
- British Association of Dermatologists, Melanocytic naevi (moles) patient leaflet (Apr 2021). For: Removal is cosmetic, histology where in doubt.
Figures are drawn from UK national guidance and published studies, and your own risk may be higher or lower. More from the British Association of Dermatologists on moles, cysts and cryotherapy.
Aftercare
Wound care advice is provided in writing at the procedure. The Waterfront nursing team is available for the first week for any wound-related concerns. Stitches, where used, are removed at 7 to 14 days, depending on the site. Your consultant remains accessible after the appointment — if anything concerns you, they will respond directly and arrange to see you as soon as needed.
Histology results are normally available within approximately two weeks. The result is communicated by the consultant who performed the procedure.
- Day of surgeryHome within the hour. Most skin surgery is under local anaesthetic.
- Next dayBack to office work. Heavy, dirty or wet jobs need a few days.
- Days 7–14Stitches out at Waterfront.
- 3–4 weeksHistology results, where a sample is sent to the laboratory.
- 12 monthsNurse reviews, dressing clinics and the treatment of any complications are included.
Typical timings. Your consultant and nurse will tailor them to you.

Very impressed by the holistic approach. I booked for a check up on one mole and was very reassured to get an all over mole body check. An annual check up is an excellent plan.
Christine Sheerin
Aug 2026 Read on Trustpilot (opens in a new tab)
Your consultants
Benign skin lesion removal at Waterfront is performed by Mr Ben Aldridge — the UK’s only consultant dual-qualified in dermatology and plastic surgery, with a PhD in skin lesion diagnostics — and by Mr Kazem Nassar, consultant plastic and reconstructive surgeon. Both are on the GMC Specialist Register. The consultant who assesses you at the consultation is the consultant who performs the removal and reviews you afterwards.
You meet your consultant at your first appointment. The same consultant plans your treatment, carries it out and sees you afterwards.


What benign skin lesion removal costs
- Consultation
- £200, with a consultant. It includes a dermoscopic examination and a same-appointment recommendation.
- Histology
- Included with every excision, so you get a laboratory diagnosis, not just a removal.
- Your quotation
- Confirmed in writing after your consultation, once the consultant has assessed the lesion.
- Paying
- Interest-free finance over 6 or 10 months is available for most skin procedures at Waterfront.
Pricing is set by the type of lesion, the method of removal, and the size of the procedure. Guide prices at Waterfront Private Hospital:
- Consultation — £200
- Skin tag removal — from £395
- Shave excision of a benign lesion (including histology) — from £595
- Removal of a small cyst or lipoma (under 2cm) — from £695
- Excision of a benign skin lesion (including histology) — from £795
- Removal of a medium cyst or lipoma — from £895
- Removal of a large cyst or lipoma (over 5cm) — £1,195 to £2,500
- Scar revision (local anaesthetic) — from £1,200
- Scar revision (general anaesthetic) — from £4,500
Each price covers the consultant’s fee, the hospital and theatre fees at Waterfront, histology (where applicable), and routine post-operative reviews. Final pricing is confirmed in writing after consultation, based on the size, site, and method required.
Waterfront Private Hospital is self-pay.

